
If your surgeon has mentioned knee replacement, the first question is usually simple: should it be a total or a partial procedure? The short answer is that a total knee replacement resurfaces the entire joint, while a partial (unicompartmental) replacement only addresses the damaged section. Which one suits you depends on how your arthritis is distributed, the state of your ligaments and several personal factors assessed by a knee specialist.
Direct answer: A partial knee replacement is generally considered when arthritis is confined to a single compartment of the knee and the ligaments are intact. A total knee replacement is used when damage affects several areas. Both aim to relieve pain, but the right choice depends on imaging findings and clinical criteria, not on preference alone.
This guide translates the medical vocabulary into clear decision criteria so you can prepare a focused conversation with your surgeon.
What is the difference between total and partial knee replacement?
The knee is divided into three sections, called compartments: the inner (medial), the outer (lateral) and the area behind the kneecap (patellofemoral). A total knee replacement (also called total knee arthroplasty) resurfaces all three compartments with metal and plastic prosthetic components. A partial knee replacement — more precisely, a unicompartmental knee arthroplasty — only replaces the damaged compartment, most often the medial one. As Prof. Etienne Cavaignac can explain in the context of knee surgery, the choice between these two procedures depends on the extent and location of the cartilage damage, as well as the condition of the remaining compartments and ligaments.
A simple analogy may help: a partial replacement is like repairing only the worn part of a tyre, while a total replacement resurfaces the whole contact surface of the joint. Both procedures share the same goal: relieving the pain of advanced knee arthritis when physiotherapy, weight management, pain medication and injections no longer bring enough relief. The most appropriate option depends on an individual assessment of the knee, the patient’s symptoms and functional needs, and the surgeon’s evaluation of the potential benefits and limitations of each technique.
Key distinctions to remember
- Total knee replacement resurfaces all three compartments of the knee.
- Partial knee replacement treats only one damaged compartment, usually the medial.
- Both procedures aim at pain relief when conservative treatment has failed.
- The terminology you may hear includes “total knee arthroplasty” and “unicompartmental knee arthroplasty”.
How do recovery and implant outcomes compare?
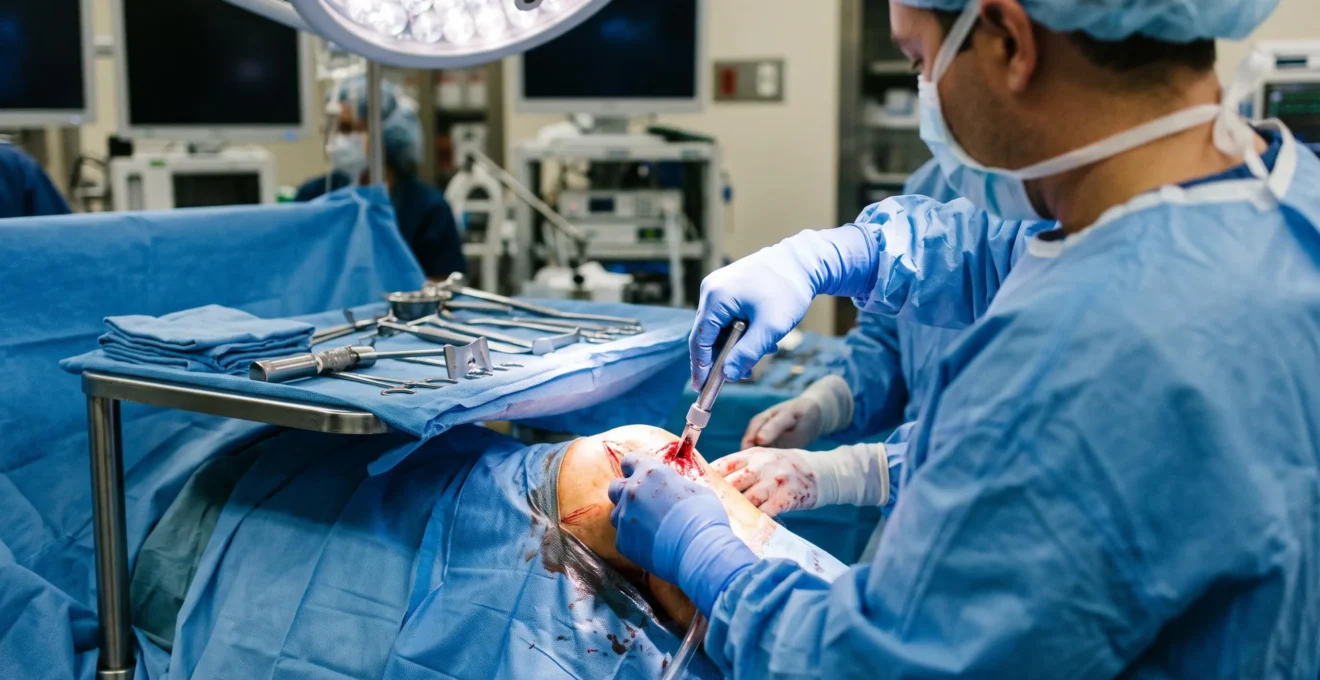
Recovery after a partial knee replacement is generally faster than after a total procedure. Because the surgery is less invasive, patients often experience less blood loss, a shorter hospital stay and quicker return to walking. A total knee replacement involves more extensive bone work and soft tissue release, which usually translates into a longer rehabilitation period before you regain full function.
Pain relief, however, can be comparable with both procedures when the patient is well selected. Long-term outcomes have been studied extensively in national registries and randomised trials. According to data published by the UK National Joint Registry, partial (unicondylar) knee replacements accounted for 14.7% of knee procedures in 2024, with the best-performing implant brands showing revision rates of 1.88% at five years and 5.03% at ten years. These figures reflect UK practice and vary with implant model, surgical volume and patient selection.
The UK TOPKAT trial, a randomised study across 27 NHS hospitals, compared both options with long follow-up. Its authors reported that, in appropriately selected patients with isolated medial compartment arthritis, partial knee replacement delivered greater quality-adjusted life years and lower healthcare costs at 10 years than total knee replacement. The study is detailed in the TOPKAT 10-year follow-up publication.
| Criterion | Total knee replacement | Partial knee replacement |
|---|---|---|
| Extent of surgery | Resurfaces all three compartments | Resurfaces one compartment only |
| Typical recovery | Longer rehabilitation | Generally quicker return to activity |
| Patient eligibility | Broad: diffuse arthritis | Restricted: single-compartment arthritis |
| Revision risk | Lower revision rate overall in registries | Higher revision rate reported in registries |
Importantly, “better” is not a universal label. Registries tend to show higher revision rates for partial replacement, while randomised trials in carefully selected patients suggest excellent outcomes. The gap reflects how strict patient selection is in real-world practice.

Who is a suitable candidate for a partial knee replacement?
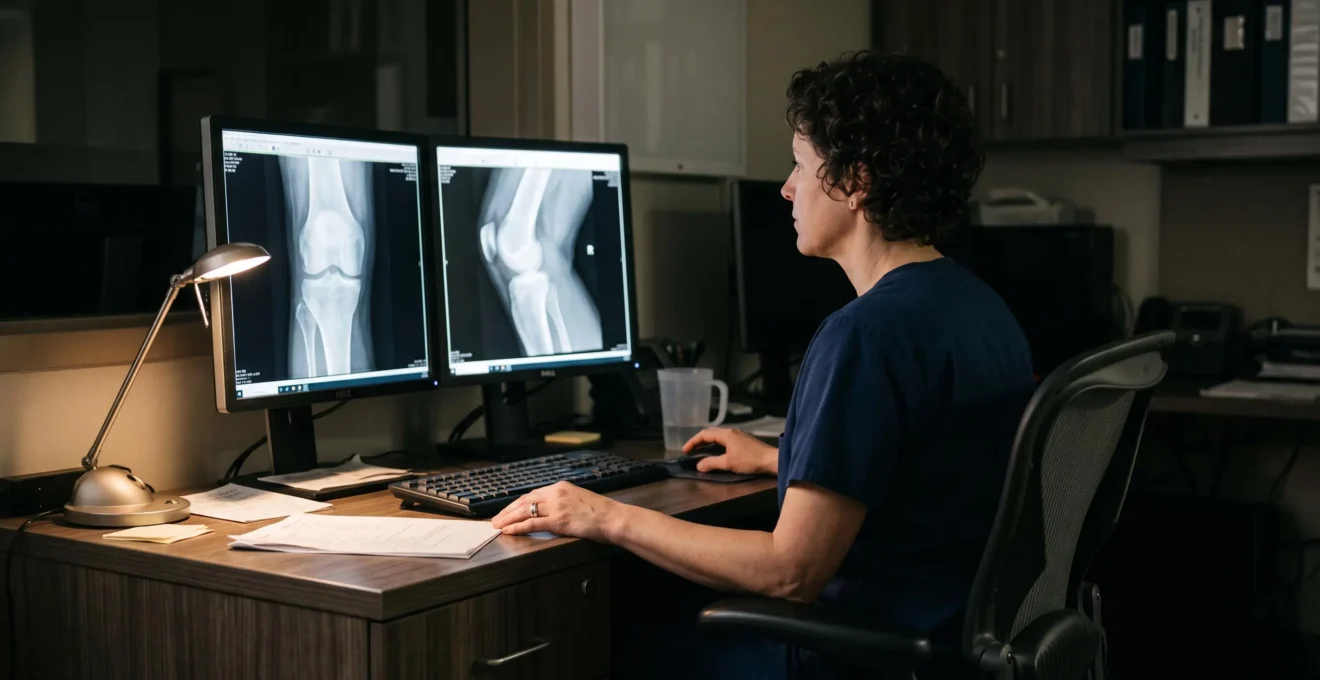
Eligibility for a partial knee replacement rests on precise criteria confirmed through examination and imaging. The core requirement is that arthritis must be limited to a single compartment, most often the medial side. If the X-rays or MRI reveal damage spread across several areas, a total knee replacement is usually recommended instead.
Other criteria assessed by the surgeon typically include:
- An intact anterior cruciate ligament, which is essential for the stability of a partial implant.
- A deformity (such as a bowed leg) that remains correctable during examination.
- A reasonably preserved range of motion, without severe stiffness.
- Body weight and activity level, considered as part of the overall assessment.
According to NICE recommendations on primary joint replacement, people with isolated medial compartmental osteoarthritis should be offered a choice between partial and total knee replacement, with the surgeon discussing the potential benefits and risks of each option. In other words, meeting the criteria opens the door to a discussion, not an automatic decision.
Profile of a typical partial candidate: a patient with pain concentrated on the inner side of the knee, isolated medial compartment arthritis on imaging, intact ligaments and a deformity that can be gently corrected by hand during examination.
Profile better suited to a total replacement: a patient with pain across the whole knee, imaging showing damage in two or three compartments, significant stiffness or a ligament deficiency.
What are the risks and limitations of each option?
Any knee replacement is major surgery. Both total and partial procedures share a set of general risks, including infection, blood clots (deep vein thrombosis), bleeding, stiffness and implant loosening over time. These risks are not identical for every patient and are discussed in detail during the pre-operative consultation.
The two options also carry specific limitations:
Partial knee replacement
- Less invasive procedure, preserving healthy bone and ligaments.
- Generally shorter hospital stay and faster early recovery.
- Often perceived as a more “natural” feeling knee.
- Risk of needing a revision if arthritis progresses in another compartment.
- Strict eligibility criteria that not all patients meet.
- Outcomes highly dependent on precise patient selection.
Total knee replacement
- Addresses arthritis across the entire joint in one procedure.
- Broad indication, suitable for most patients with advanced arthritis.
- Well-documented long-term outcomes in national registries.
- More extensive surgery with longer rehabilitation.
- Greater soft tissue impact and often more early post-operative pain.
- Does not fully restore the sensation of a native knee.
Revision is not failure, but a real possibility: national registries typically report higher revision rates for partial knee replacements than for total ones. In many cases, a partial can be revised to a total replacement later, but this is still a second operation that should be factored into the decision.
Neither option is universally “better”. The best procedure is the one that matches your anatomy, your arthritis pattern and your expectations, discussed openly with your surgeon.
When should you consult a knee specialist?
You should consider a specialist consultation when knee pain starts to limit everyday activities — walking, climbing stairs, sleeping, working — despite months of appropriate conservative treatment such as physiotherapy, weight management, pain medication or injections. Advancing age alone is not a reason to operate; persistent, disabling symptoms are.
Only a dedicated clinical examination combined with up-to-date imaging (standing X-rays, sometimes MRI) can determine which compartments of your knee are affected and whether a partial procedure is possible. Online information, including this article, can prepare the conversation but cannot replace a personalised assessment.
- Persistent pain despite treatment:Knee pain lasting more than several months despite physiotherapy, pain relief and injections.
- Functional limitations:Difficulty walking, standing or sleeping because of the knee.
- Visible deformity or instability:Progressive bowing of the leg, giving way, or recurrent swelling.
- Previous unclear advice:You have been told surgery may be needed but want a clear comparison of options.
To make the most of your appointment, prepare a short checklist: when the pain started, what makes it worse, what treatments you have already tried, which activities you want to recover and any questions you have about total versus partial options. Bring your recent imaging if available.
Can I have a partial knee replacement if only one part of my knee is damaged?
Possibly, but single-compartment damage is only one of the criteria. Your surgeon will also check the state of your ligaments, your range of motion, the correctability of any deformity and your overall profile before confirming whether you are a candidate.
Is recovery faster after a partial knee replacement than after a total one?
In general, yes. Partial replacement is less invasive and often associated with a shorter hospital stay, less blood loss and quicker return to walking. Individual recovery still depends on your age, overall health, rehabilitation and the specifics of your surgery.
What happens if a partial knee replacement fails over time?
If the arthritis progresses in another compartment or the implant wears out, a revision surgery may be considered, often converting the partial into a total knee replacement. This revision is a dedicated procedure and should be discussed in advance as part of the long-term plan.
Will a partial knee replacement last as long as a total one?
Long-term data from national registries generally show higher revision rates for partial compared with total replacements, although the best-performing partial implants achieve very good survival. Durability depends strongly on patient selection, surgical technique and implant choice.
The decision between total and partial knee replacement is rarely a matter of personal preference alone: it rests on the anatomy of your arthritis, the condition of your ligaments and your functional goals. A thorough consultation with a knee specialist, supported by recent imaging, is the only reliable way to know which option fits your situation. Taking time to prepare questions and understand both procedures will help you enter that discussion more confidently and leave it with a clearer plan.